
Opinion|Videos|August 4, 2026
Differentiating Second-Line Agents and Chemotherapy Rechallenge in EGFR-Mutated Non-Small Cell Lung Cancer: Datopotamab Deruxtecan
Author(s)Ticiana A. Leal, MD
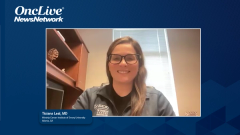
Dr. Leal compares amivantamab plus chemotherapy (MARIPOSA-2) with datopotamab deruxtecan (from the pooled TROPION-Lung01 and TROPION-Lung05 analysis) in the second-line setting for EGFR-mutated NSCLC. Datopotamab deruxtecan, now FDA-approved for previously treated patients, demonstrated promising median PFS, OS of approximately 15 months, and notable CNS activity with an intracranial response rate of approximately 40%. As a monotherapy administered intravenously once every 3 weeks, she describes it as straightforward to incorporate clinically. Distinct toxicities associated with this TROP2-directed antibody-drug conjugate with a topoisomerase 1 inhibitor payload include mucositis (managed with prophylactic dexamethasone mouthwash), interstitial lung disease requiring close symptom monitoring, and ocular toxicities, predominantly dry eyes, mitigated with prophylactic eye drops and baseline ophthalmologic evaluation.
Advertisement
Episodes in this series
Dr. Leal compares amivantamab plus chemotherapy (MARIPOSA-2) with datopotamab deruxtecan (from the pooled TROPION-Lung01 and TROPION-Lung05 analysis) in the second-line setting for EGFR-mutated NSCLC. Datopotamab deruxtecan, now FDA-approved for previously treated patients, demonstrated promising median PFS, OS of approximately 15 months, and notable CNS activity with an intracranial response rate of approximately 40%. As a monotherapy administered intravenously once every 3 weeks, she describes it as straightforward to incorporate clinically. Distinct toxicities associated with this TROP2-directed antibody-drug conjugate with a topoisomerase 1 inhibitor payload include mucositis (managed with prophylactic dexamethasone mouthwash), interstitial lung disease requiring close symptom monitoring, and ocular toxicities, predominantly dry eyes, mitigated with prophylactic eye drops and baseline ophthalmologic evaluation.
Given that the datopotamab deruxtecan data were generated in a post-chemotherapy population, Dr. Leal favors amivantamab-based combination therapy (incorporating subcutaneous amivantamab) for patients who have not yet received platinum-based chemotherapy.
She also discusses an exploratory FLAURA2 analysis examining chemotherapy rechallenge after progression on osimertinib plus chemotherapy. Among patients with a prolonged chemotherapy-free interval (median osimertinib monotherapy duration exceeding 30 months after completing induction), 19% received a pemetrexed-containing regimen at progression, achieving a 3-year OS rate of 77% with a median pemetrexed-free interval of nearly 20 months. She considers these findings supportive of established clinical practice, stating that platinum rechallenge is reasonable when the platinum-free interval exceeds approximately 6 months to 1 year, and reassuring for incorporating chemotherapy rechallenge after extended benefit from osimertinib-chemotherapy combinations.
Advertisement
Related to this article

Benjamin Weinberg, MD, discusses the FDA approval of daraxonrasib, RASolute 302 survival data, safety considerations, and future RAS-targeted therapies in pancreatic cancer.

Half of lenalidomide-refractory patients with 1 to 3 prior lines remained alive and progression free at least 5 years after a single cilta-cel infusion.

Andrew Kuykendall, MD, discusses the FDA approval of rusfertide and how to apply it in clinical practice for polycythemia vera management.
An NDA seeks FDA approval of savolitinib plus osimertinib for EGFR-mutated NSCLC with MET overexpression or amplification after EGFR TKI therapy.

Jason Hafron, MD, discusses the emotional, clinical, and financial burden of false positive cancer screening results and improved risk stratification.

Raajit K. Rampal, MD, PhD, discusses JAK inhibitor choice in cytopenic myelofibrosis, emerging combinations, and anemia-directed agents.
The sNDA for elinzanetant seeks FDA approval for moderate-to-severe vasomotor symptoms in women receiving endocrine therapy for HR-positive breast cancer.
The NMPA has approved of pirtobrutinib in treatment-naive and previously treated CLL/SLL.
Advertisement
Advertisement
Trending on OncLive
1
Ifinatamab Deruxtecan BLA Voluntarily Withdrawn in Previously Treated Extensive-Stage SCLC
2
China's NMPA Approves Pirtobrutinib Across CLL
3
FDA Grants Priority Review to Elinzanetant for Endocrine Therapy–Associated Vasomotor Symptoms in HR+ Breast Cancer
4
Long-Term PERSEUS Data Confirm Durable PFS Benefit With D-VRd in Transplant-Eligible Newly Diagnosed Myeloma
5